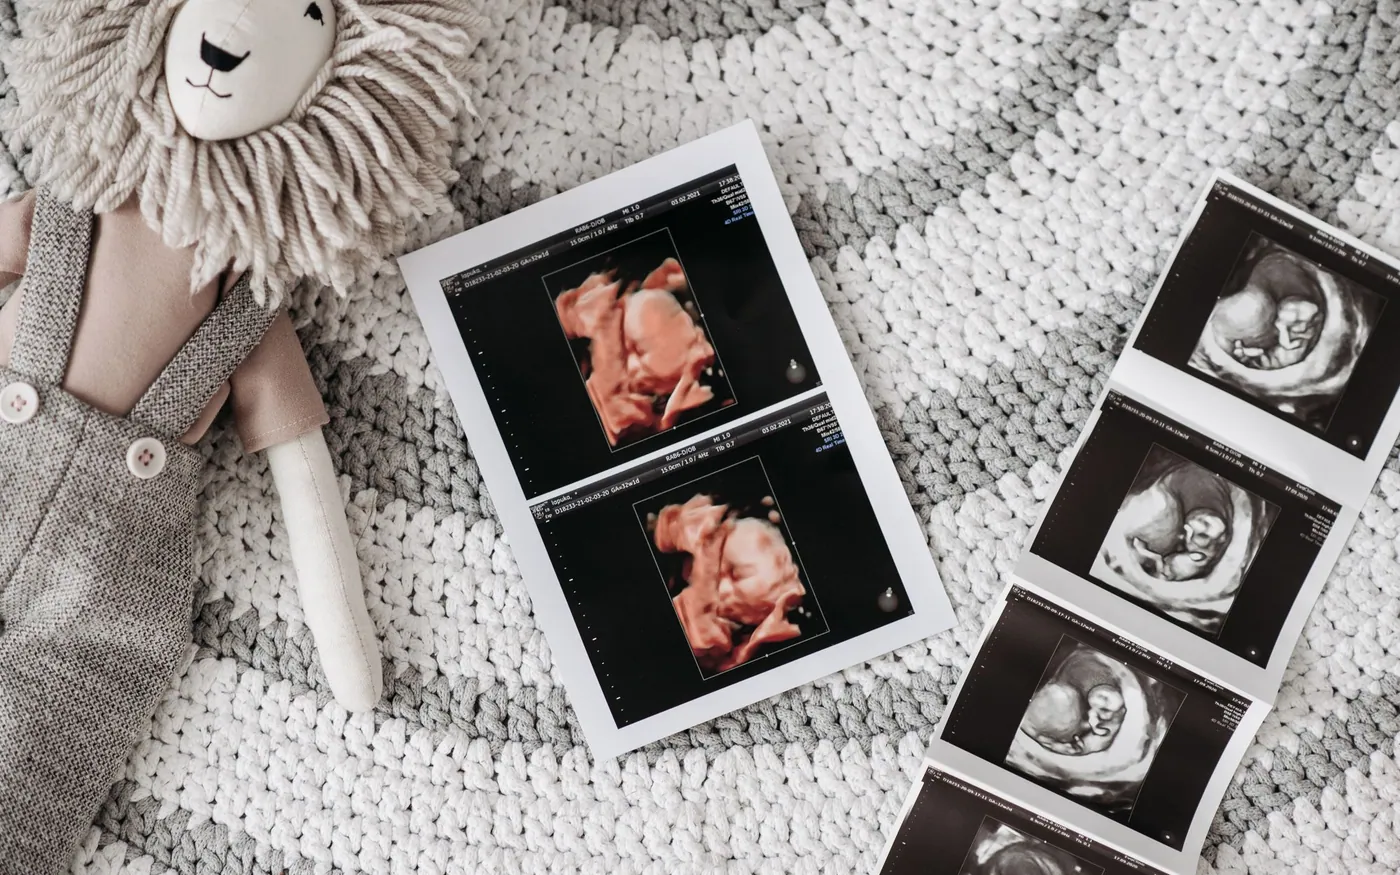
An appointment slip can make prenatal tests look like a list of tasks to finish. They do not all do the same job. Some assess the pregnant person's health, some estimate the chance of a fetal condition, and others investigate a specific diagnosis. Understanding the question behind a test helps with informed decisions, preparation and follow-up. Your care team should adapt this stage-based map to gestational age, history and testing already completed.
The short version
- 01
Screening estimates probability; it does not establish a diagnosis.
- 02
A normal result answers only the question within that test's scope.
- 03
Every result needs an owner and a clear next step.
Jump to the part you need
The first visit: establish the starting point
The history conversation is part of the assessment, not merely a delay before blood sampling. Period dates, ongoing conditions, previous pregnancies and family history can change the tests offered. Early checks commonly include a blood count, blood group and Rh status, alongside relevant infection screening such as hepatitis B, HIV and syphilis. Tu Du describes these in its antenatal guidance; your clinician determines the applicable plan.
Ask: “How could this result change care for me or the baby?” Blood grouping is not a fetal-anomaly test, and ultrasound does not replace all blood testing. When bringing results from elsewhere, retain the date, units and laboratory identity rather than copying only “normal”. This makes previous work intelligible and helps the new team distinguish necessary reassessment from duplication caused by incomplete records.
Early pregnancy: choose a deliberate screening pathway
Serum screening, nuchal-translucency ultrasound and cell-free DNA testing, often called NIPT, are not three certificates to collect. They have different roles and limitations in assessing chromosome-related risk. ACOG's 2026 guidance emphasises pretest counselling and the choice to accept or decline. Ask which conditions the proposed approach investigates and how it relates to testing already performed, rather than assuming that more separate packages mean more certainty.
Some assessments have timing windows, so discuss them early rather than waiting until the day you want the test. If a window has passed, do not assume there are no remaining options or buy a late package to “replace” the missed one. Ask: “At this gestational age, what can still be assessed, and how should we interpret the result?” Timing belongs to the specific test, not just the trimester label.
Mid-pregnancy: ultrasound examines structure, not everything
The mid-pregnancy anatomy examination assesses fetal structures. It remains relevant after a low-risk chromosome screen because anatomy and chromosomes are related but different questions. Know what the examination is intended to assess and who will explain the report. A clear image of the baby's face may be memorable, but it is not the measure of whether a medical structural examination has been completed.
If another examination is booked, ask why instead of translating “repeat” into “something is wrong”. Completing an unanswered part of an examination and following a finding are different purposes. Ask the clinician to identify what has been answered, what remains uncertain and what the next visit should resolve. A new calendar entry is useful only when you also understand the question attached to it.
Around 24 to 28 weeks: assess glucose handling
Gestational diabetes may have no obvious symptoms. CDC and Tu Du both identify 24 to 28 weeks as a common testing period, with earlier assessment for some people. An oral glucose tolerance test, or OGTT, examines the body's response to the glucose used in the procedure. It is not a test of dietary virtue. An elevated result is clinical information, not a judgement about your character.
Get the testing site's instructions about fasting, water, morning medicines and how long to stay. Do not fast for every blood test or restrict carbohydrates to improve the number. If you vomit during the procedure, tell staff so they can decide what follows. Plan transport and work around the actual sampling process rather than squeezing a waiting-dependent appointment between tightly scheduled meetings.
Later pregnancy: make results useful for birth
Blood-pressure checks, urine testing or repeat blood counts may continue according to the care plan. Normal early results do not exclude conditions developing later. Near birth, ask about group B streptococcus testing where applicable, what its result means and how the receiving birth team will see it. Avoid transferring one hospital's timetable to everyone, particularly when changing providers or managing an individual condition.
A portable record should contain the actual reports, not only an app's summary screen. Keep an abnormal result alongside its explanation and follow-up plan so it does not become an isolated red number. If results are pending when care changes, establish who will report them and how. Good handover is not the largest stack of paper; it is preserving information that may matter during birth.
When a result is high risk or inconclusive
A high-risk screen does not mean the fetus definitely has the condition. ACOG distinguishes screening from diagnostic procedures such as chorionic villus sampling and amniocentesis. Discuss appropriate confirmation, benefits, limitations and procedural risks before deciding. Likewise, a low-risk result is not a guarantee against every possible health problem. Other elements of antenatal care still have separate purposes and should not disappear behind one reassuring report.
“Pending” and “insufficient information” are not negative results. For a confusing report, try: “Please explain what is known, what remains unknown and what the next options are. I need counselling before deciding.” Arrange a real conversation rather than relying on a photograph in a chat group. The testing pathway succeeds when information becomes a care plan you understand, not when every box is ticked.
Practical checklist
- Before testing, know the purpose, preparation and result contact.
- Bring dated reports with units when changing care providers.
- Include pending results in the follow-up plan.
From the guide to your next step
How NIMO built this guide
NIMO writes and localizes each guide for Vietnamese families, then checks key facts against the official references below. The links support the guide; they are not the guide itself.
General health information · Checked against official sourcesFor symptoms or treatment decisions, confirm with an appropriate health professional.Next review · Dec 5, 2026



